 Oct 26 2026
 CBCT segmentation
How to Build Training-Ready CBCT Datasets: Annotation Types, Common Challenges, and Best Practices
CBCT annotation is the process of labelling cone-beam computed tomography scans so that an AI model can learn to recognise teeth, bone, nerves, sinuses, and pathology. A training-ready CBCT dataset needs the right label type for the task, a written annotation protocol, expert annotators, and a layered quality check. Without these, even a large dataset produces an unreliable model.
This guide explains the main annotation types, the challenges teams meet most often, and the practices that separate a usable dataset from an expensive pile of scans.
Key Takeaways
- CBCT annotation is the foundation of any dental or maxillofacial AI model.
- The label type (classification, bounding box, landmark, or voxel-level segmentation) must match the clinical task.
- Metal artifacts, thin structures, and annotator disagreement are the biggest quality risks.
- A written SOP, clinically aware annotators, and multi-stage QC make a dataset training-ready.
What Is CBCT Annotation and Why Does It Matter for AI?
Cone-beam computed tomography (CBCT) is a standard imaging method in dental and orofacial care. It produces 3D volumes of the jawbones, teeth, sinuses, and neurovascular canals.
A deep learning model cannot read these volumes on its own. It learns from examples where an expert has already marked the structures of interest. Those labels are the ground truth.
The quality of that ground truth sets the ceiling for model performance. Manual labelling is slow and needs real expertise. Public research datasets show the scale involved. The ToothFairy2 dataset, for example, provides voxel-level 3D annotations for 42 maxillofacial classes, and it was built to support automated segmentation research.
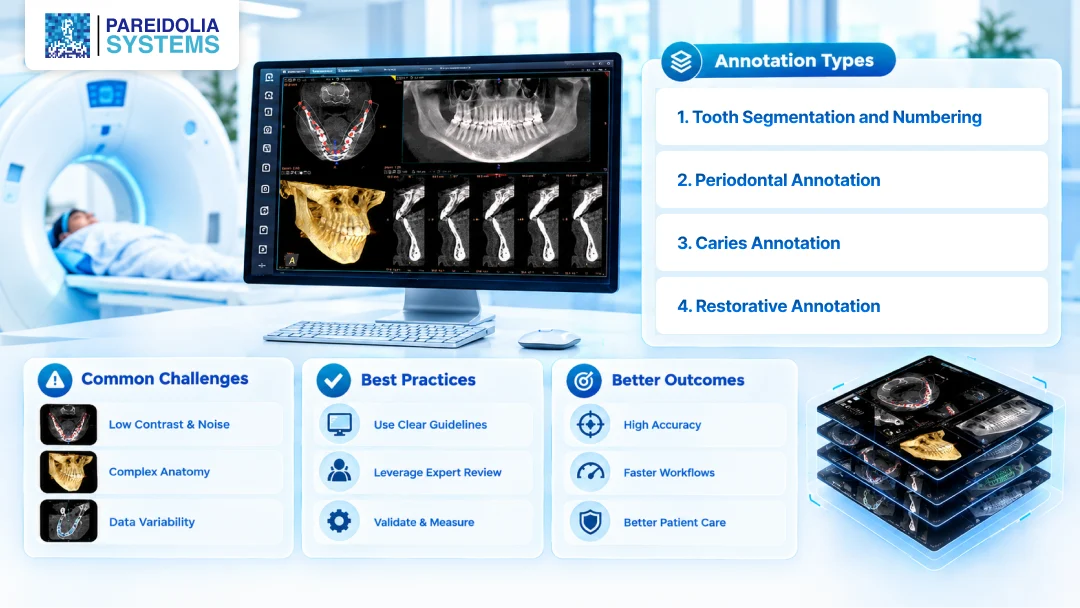
What are the Main Types of CBCT Annotation?
Each dental AI task needs its own kind of label, and the wrong choice wastes budget and caps what your model can learn. Here are the six types most teams request
1. Tooth Segmentation and Numbering
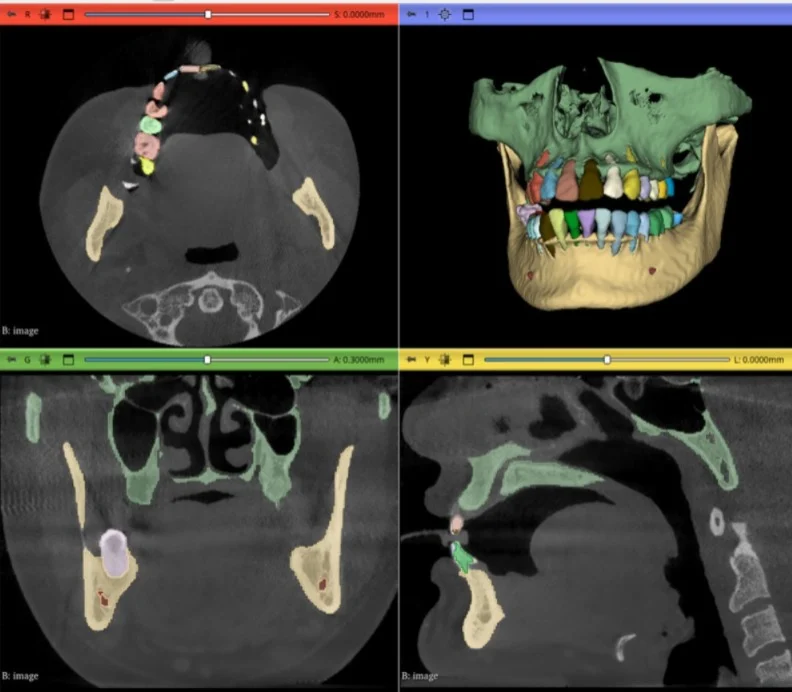
Each tooth is outlined as a separate 3D object (crown and root) and assigned a tooth number, usually in FDI notation. It underpins automated charting, implant planning and orthodontic analysis. Crowded arches, missing or extra teeth, third molars and metal streaking are the usual trouble spots, so numbering rules for these cases should be written down up front.
2. Periodontal Annotation
Annotators mark alveolar bone, crestal bone level, the CEJ, furcation involvement, and bone defects as masks or measurement points. Findings here are subtle, which makes clinician-defined criteria essential.
3. Restorative Annotation
Crowns, fillings, root canal fillings, posts, bridges, and implants are labeled so the model can separate real anatomy and pathology from restorations and artifacts. Dense materials create streaks that can hide nearby structures, so consistency on these labels affects everything around them.
4. Caries (Cavity) Annotation
Lesion location, extent, tooth surface, and often severity are marked. Early caries are harder to see on CBCT than on bitewings, particularly beside restorations. Strict criteria, dentist-level review, and a clear policy for uncertain findings keep the labels trustworthy.
5. Pathology Annotation
This covers periapical lesions, cysts, odontogenic tumors, root resorption, fractures, impacted teeth, and sinus findings, labeled as boundaries, types, or measurements depending on the task.
6. Anatomical Structures and Landmarks
The mandibular canal, mental foramen, maxillary sinus, jawbone, TMJ, and airway guide surgical and orthodontic planning. The canal is often traced as a centerline or segmented as a mask, and landmark points support cephalometric measurements.
What Are the Common Challenges in CBCT Annotation?
Most dataset failures trace back to a handful of recurring problems.
Metal Artifacts and Noise
Implants, crowns, and amalgam fillings create streaks and scatter. These obscure neighbouring structures and confuse annotators and models alike. Artifact-heavy scans need clear rules for what to label and what to flag.
Thin and Low-Contrast Structures
The mandibular canal and thin cortical bone walls are hard to see. Small boundary errors on a thin structure represent a large share of its volume. One published implant-planning study found that differences between manual labels and model output often came from annotators skipping narrow bone regions and smoothing the surface by hand. Annotation choices directly shape what the model learns.
Inter-Annotator Variability
Two experts can draw the same boundary differently. Without a shared definition, this inconsistency becomes label noise, and the model learns the noise.
Scanner and Protocol Differences
Voxel size, field of view, and reconstruction settings vary between machines and clinics. A dataset from a single device may not generalise to others.
Sparse or Incomplete Labels
Annotating all anatomy in every scan is costly. Partial labelling is common, but it must be documented. Otherwise, the training pipeline may treat missing labels as background.
Time and Scale
A single full-volume segmentation can take a long time. Large projects need a team that can scale without a drop in consistency.
What are the Best Practices for Training-Ready CBCT Datasets?
Most problems in CBCT datasets trace back to decisions made before labeling began and to how the work was reviewed afterward. These are the practices that tend to hold up in training.
Documented Annotation SOP
Every class, boundary rule, and edge case is defined up front, along with scan inclusion and exclusion criteria and example images for artifacts, missing teeth, and restorations. A clear SOP is the most effective way to reduce variability.
Clinical Awareness in Annotation
Annotators who understand dental anatomy make better decisions on ambiguous boundaries. Regular training and calibration sessions keep labels consistent as a project grows.
Quality Control as a Separate Stage
Dedicated reviewers, independent of the annotators, usually work through a layered process:
- Annotator self-review against the SOP
- Peer or senior review of a defined sample
- Overlap metrics, such as Dice score, on doubly labeled cases
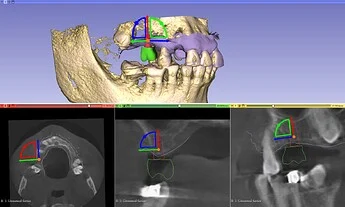
- Visual checks in axial, sagittal, and coronal views
- Feedback loops that update the SOP as new edge cases appear
AI-Assisted Pre-Labeling, With Expert Correction
Model-generated pre-labels can speed up segmentation. Expert correction keeps one model’s errors from becoming the next model’s training data.
Balanced and Documented Datasets
Variety in anatomy, age groups, restorations, missing teeth, and scanner types supports generalization. Metadata and documented limitations make clear what the dataset can and cannot support.
Patient Data Protection
DICOM files are de-identified, with applicable privacy rules such as HIPAA, GDPR, and GCP followed throughout the workflow.
How Does Pareidolia Support CBCT Annotation Projects?
Pareidolia Systems turns complex medical images into AI-ready datasets through expert annotation. The workflow is simple and transparent:
- Dataset submission: You share the scans, and we study your requirements.
- SOP drafting: We draft the annotation SOP and agree on inclusion and exclusion criteria.
- Expert annotation: Clinically trained annotators label and segment the data.
- Inter-annotator agreement: Every scan is labeled against the same SOP, and agreement is measured with Dice score and Cohen’s kappa. Disagreements are resolved through adjudication.
- Domain expertise: Annotators with dental and clinical training understand the anatomy they label, which means fewer implausible labels and more reliable ground truth.
- Platform-agnostic: We work across various annotation platforms such as 3D Slicer, ITK-SNAP, Mimics, CVAT or in-house platforms and deliver in DICOM, NIfTI or NRRD.
- Dentist/Radiologist-backed QA: A qualified radiologist/Dentist reviews labels in a dedicated QA stage, catching errors before delivery so the data is ready for training and validation.
- 24/7 availability: Around-the-clock workflows keep large CBCT batches moving across time zones with predictable turnaround.
. You can explore our related services:
- Annotation of medical images
- Medical image segmentation
- Quality control in medical imaging
- 3D model creation
- Dental AI expertise
Whether you are running a pilot or a large rollout, the team scales with you and keeps communication open at every step.
FAQs About CBCT Annotation
-
What is CBCT annotation?
CBCT annotation is the labelling of cone-beam CT scans by trained experts so AI models can learn from them. Labels can be classes, boxes, landmarks, centerlines, or voxel-level masks, depending on the clinical task.
-
What is the difference between CBCT annotation and CBCT segmentation?
CBCT annotation is the broad term for any labelling of CBCT data. CBCT segmentation is one type of annotation. It outlines the exact 3D shape of a structure by labelling each voxel.
-
Which structures are usually segmented in CBCT scans?
Common targets include individual teeth, jawbones, the mandibular canal, maxillary sinuses, dental restorations, and implants. Larger datasets may cover dozens of maxillofacial classes.
-
How many CBCT scans do I need to train a model?
It depends on the task and model. Public benchmarks range from a few dozen carefully labelled volumes to hundreds. Label quality and diversity often matter more than the raw volume.
-
How do you ensure CBCT annotation quality?
Use a written SOP, calibrated expert annotators, a pilot batch, and multi-stage review with agreement metrics such as the Dice score. Update the SOP whenever new edge cases appear.
-
Can AI-assisted tools replace manual CBCT annotation?
They can speed it up, but expert review is still essential. Unchecked pre-labels risk carrying errors into the training dataset.
- What file formats are used for CBCT datasets?
Scans are typically stored as DICOM. Labels commonly exported as NIfTI or similar volumetric mask formats.
Conclusion
A training-ready dataset does not happen by accident. It comes from choosing the right label type, writing clear rules, using clinically aware annotators, and checking quality at every stage. Strong CBCT annotation and precise CBCT segmentation give your model the ground truth it needs to perform in real clinical settings.
Ready to build your CBCT dataset? Book a free demo or schedule a 30-minute meeting with the Pareidolia team.